Why Some Treatments Need Central Access
The first sign may be surprisingly ordinary: an arm that has been poked several times, feels sore, or no longer gives nurses a dependable vein. Small peripheral IVs work well for many short treatments, but they can become difficult when medication must be given repeatedly, in larger amounts, or over several days. Some medicines and concentrated fluids may also irritate the smaller veins, causing burning, tenderness, or swelling if the access does not hold up.
A central line places the tip of the catheter in a larger vein, where treatment can be delivered more consistently and blood samples may be easier to obtain. That added reliability can reduce repeated needle attempts, but it does not make the situation risk-free. Placement introduces concerns about bleeding, accidental injury, or the line sitting in an unexpected position. Once it is in place, discomfort, drainage, swelling, fever, or a change in how it functions may be worth mentioning promptly. The reason for central access is usually practical, yet its benefits must be weighed against the care and monitoring it requires.
What Makes Central Lines Different From IVs
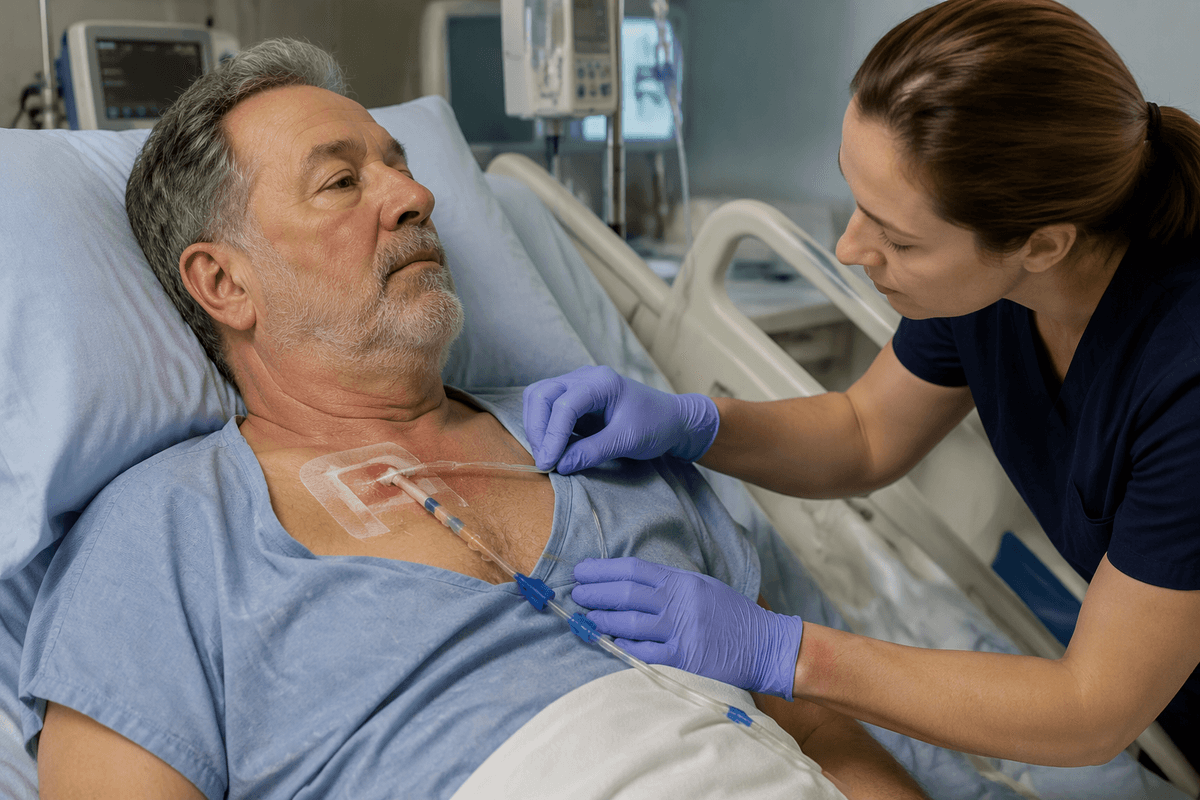
An ordinary IV may look similar at the skin, but its catheter usually ends in a smaller vein in the hand or arm and is generally used for shorter-term treatment. Central lines follow a longer route into a larger vein, allowing certain medicines, fluids, or nutrition to enter the bloodstream where they are rapidly diluted. This setup becomes useful when peripheral veins are fragile, need repeated access, or cannot safely tolerate a particular solution.
Greater depth also makes central-line care more involved than simply placing a tube. Position matters, and the opening where the line enters the skin creates another possible route for infection. Blockage, displacement, discomfort, or changes in blood flow may cause other problems, including swelling. New tenderness, drainage, fever, swelling in the arm or neck, or an unexpected change in flow should therefore be reported to the care team rather than dismissed as routine discomfort.
The Underlying Pattern Behind Line Placement
After another difficult attempt, the reason for a central line may seem to be simply that the veins are “bad.” Often, the pattern is broader: treatment is expected to continue, the medication may be harsh on smaller veins, or blood draws and infusions are happening so often that each new IV becomes less dependable. A line may therefore be chosen not because one arm vein has failed, but because repeated access is becoming an ongoing part of care.
That decision still involves uncertainty. A central line can make treatment steadier, yet its safety depends on where the tip sits, how long it remains, and how carefully it is handled. A line that once worked easily may later feel painful, stop flushing, or cause swelling near the arm, chest, or neck. Drainage, increasing redness, fever, or a change in the flow may reflect a problem that is easier to address when reported early. The device solves one access problem while creating a new need to watch the surrounding pattern.
When Convenience Creates New Uncertainty
When the line works smoothly, it can fade into the background of daily care. Medicines may run without repeated needle sticks, and blood tests may take less time. That convenience can also make small changes easier to dismiss. A little pulling during movement, mild soreness after handling, or a brief pause in the infusion may seem like routine irritation, especially when the line has been useful for several days.
A central line depends on more than its presence. Its position, the condition of the surrounding skin, and each connection or dressing change can affect how safely it functions. New swelling, persistent discomfort, leaking, drainage, redness, fever, or resistance when the line is used should not automatically be treated as harmless inconvenience. These signs may have simple explanations, but they can also point to irritation, blockage, movement, infection, or a change in blood flow. Because the cause is not always visible, describing when the change began and how it affects the line gives the care team useful information.
Risks That Develop During Placement
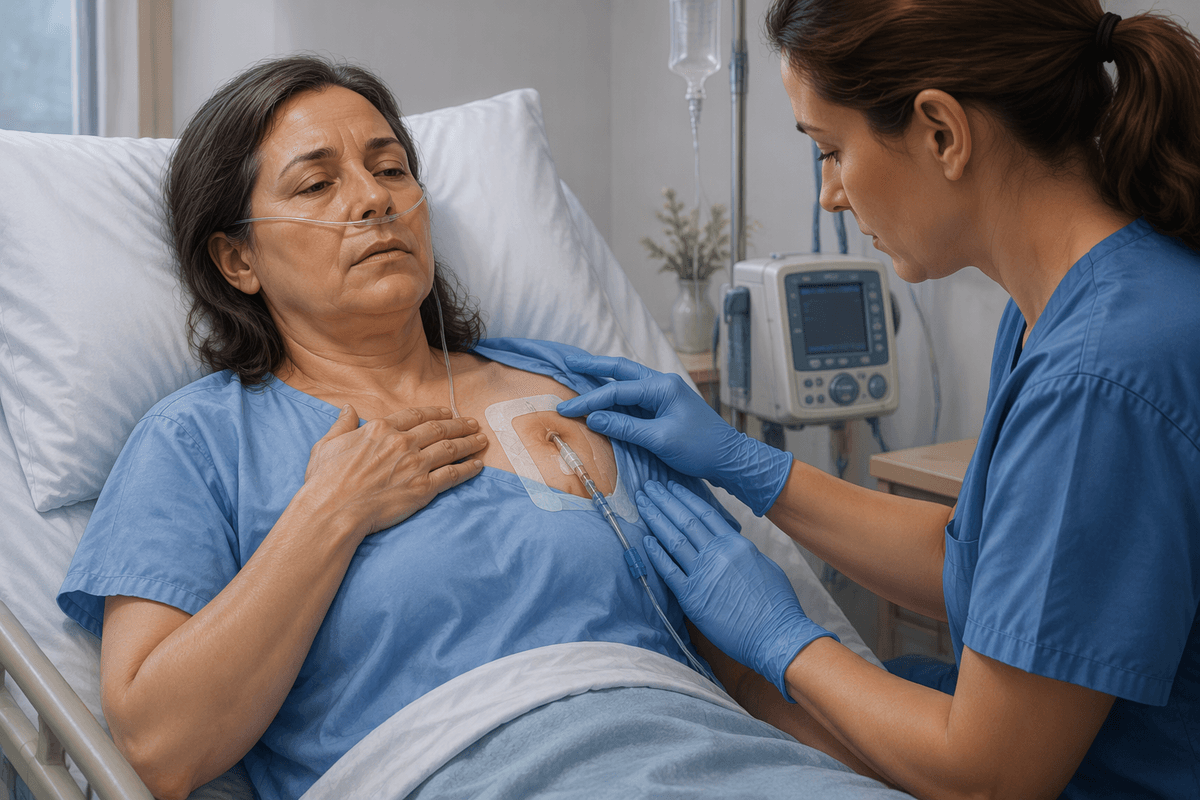
The skin may feel numb at first, followed by pressure, tugging, or a brief sharp sensation as the line is guided into place. Even when placement is routine, the path to a larger vein passes near structures that can be irritated or injured. Bleeding, bruising, or soreness around the insertion site may occur, and in some situations the catheter can enter at an unexpected angle or sit in a position that is not suitable for treatment.
That is why the line may be checked before it is fully used, sometimes with imaging or other confirmation. A change in breathing, chest discomfort, unusual dizziness, or rapidly increasing swelling during or soon after placement deserves immediate attention from the care team. Not every sensation signals a serious problem, and local tenderness can be part of the procedure, but symptoms that intensify rather than settle are harder to explain away. Placement can improve access quickly, yet the early period requires attention to both how the person feels and how the line functions.
Problems That Can Appear Afterward
A few days later, the line may be less noticeable, which is when gradual problems can be overlooked. The skin may become increasingly tender or red, the dressing may loosen, or a small amount of drainage may appear. Fever, chills, or feeling unusually unwell can occur for many reasons during hospital care, so they do not automatically point to the line, but they are still worth reporting when they occur with changes at the site. Infection is one concern, particularly when the area becomes more painful or the redness spreads.
The line may flush with more resistance, stop allowing blood to be drawn, leak during use, or cause swelling in the arm, chest, neck, or face. These changes may relate to a kink, movement, blockage, irritation, or a clot affecting nearby blood flow. A line can remain partly usable while a problem is developing, making the change easy to minimize. New discomfort, altered flow, or swelling should therefore be described rather than tested repeatedly or ignored, especially if the pattern continues.
Balancing Access Benefits Against Ongoing Risks
When a central line is working well, its value is often clearest in the small routines: treatment continues without repeated needle attempts, irritating medicines can be delivered more reliably, and blood tests may require fewer sticks. Those benefits can matter greatly when veins are fragile or care is expected to continue. They do not remove the need for observation, however. The line still depends on stable positioning, clean handling, and a surrounding area that remains comfortable and intact.
The balance can shift if the device becomes painful, swollen, damp, red, or difficult to use. A small change may come from movement or minor irritation, while another may reflect infection, clotting, blockage, or a line that is no longer positioned as expected. It may be impossible to tell the difference by appearance alone, and repeatedly testing the line can make the situation harder to assess. Reporting what changed, when it began, and whether treatment or movement affects it gives the care team a clearer picture. Central access can solve an important treatment problem, but its ongoing safety is part of the treatment itself.











